
Lesson visuals · Diagrams v2
Pictures that teach — the professional set
Every figure below is a professionally drawn, openly licensed medical illustration or clinical photo — Blausen Medical, OpenStax, Servier-grade sources — with the license recorded under each card. No hand-drawn art.
Skin integrity
Pressure injury — the stages, in real clinical photos
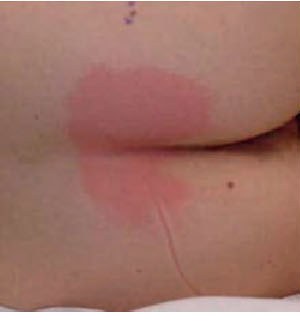
Stage 1Intact skin · non-blanchable redness over a bony prominence
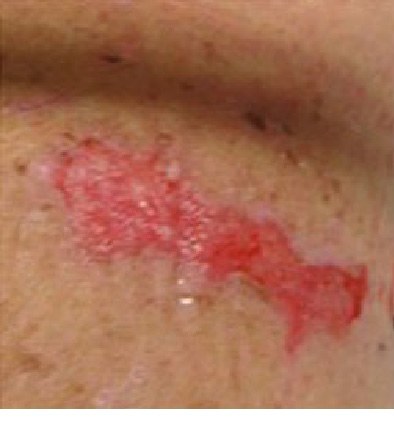
Stage 2Partial-thickness · pink, moist bed or a blister — no fat visible
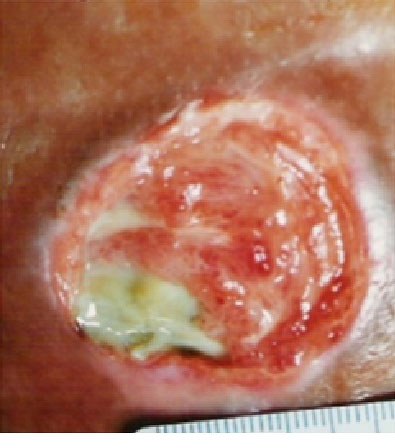
Stage 3Full-thickness · fat visible — bone, tendon, muscle NOT exposed
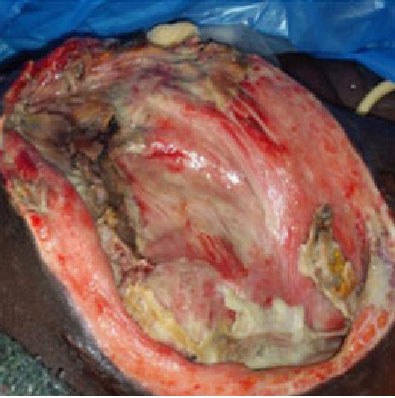
Stage 4Full-thickness · muscle, tendon or bone exposed
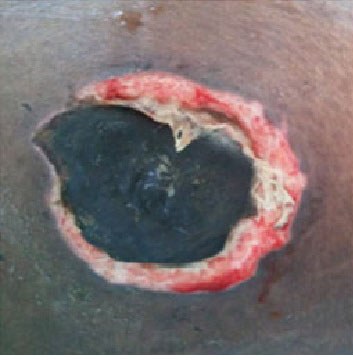
UnstageableBed hidden by slough or eschar — depth cannot be judged until it is cleaned
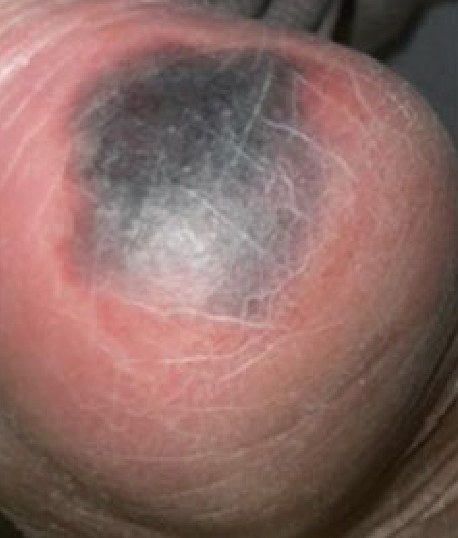
Deep tissue injuryIntact skin, deep red–purple — the damage starts deep, at the bone–muscle layer
These are real wound photographs — the same way nursing textbooks teach staging. Stage by depth, never by size.
Stage by depth, not by size. A small sore can be Stage 4 if it reaches bone — and a wound covered by eschar cannot be staged at all until the dead tissue is removed.
Photos: Dweekat et al., International Journal of Environmental Research and Public Health, CC BY 4.0 — via OpenStax Medical-Surgical Nursing §28.3, Figures 28.5(a)–28.10 (panel (a) photographs only).
Burns
Burns — depth of the burn
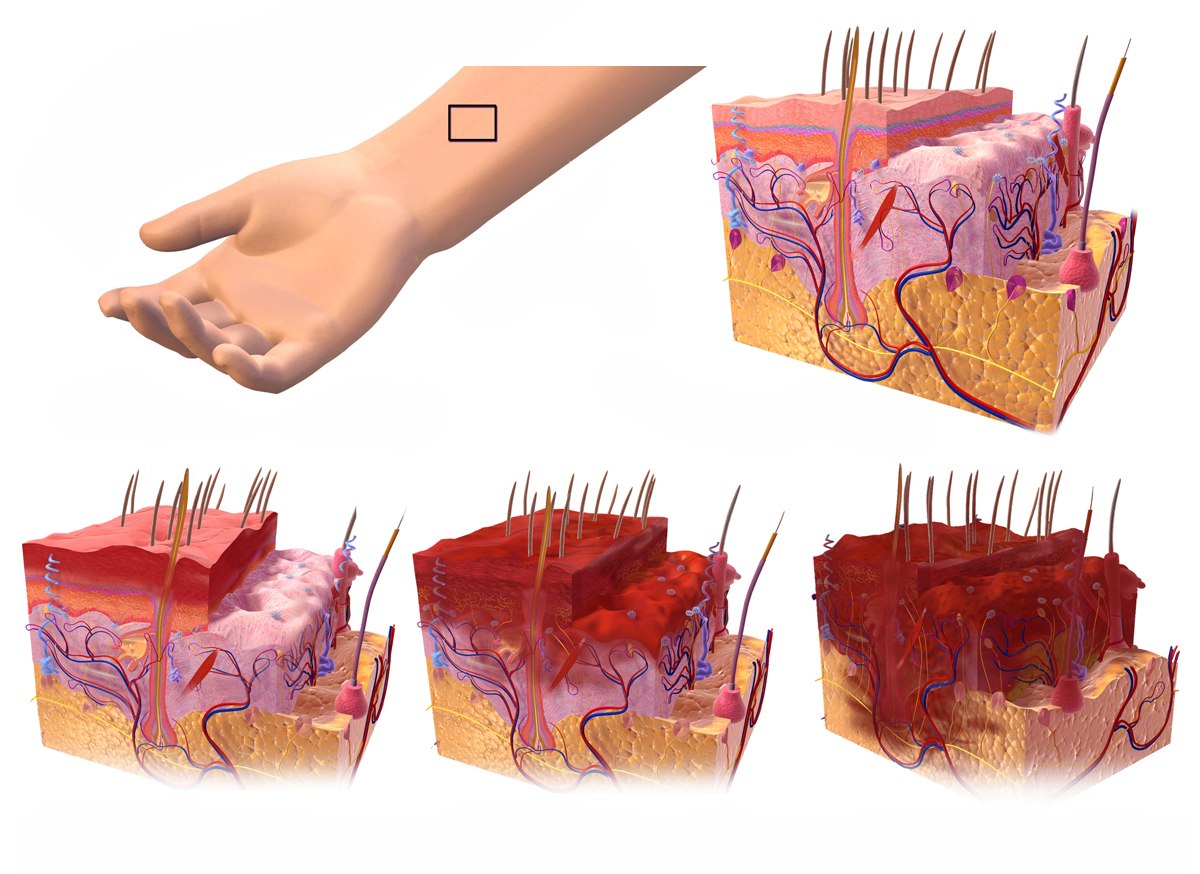
Normal skin
1st degreesuperficial
2nd degreepartial-thickness
3rd degreefull-thickness
1st · superficial
Epidermis only · red, painful, no blisters · heals in about a week
2nd · partial-thickness
Into the dermis · blisters, moist, very painful · heals in about 2–3 weeks
3rd · full-thickness
All layers destroyed · white, brown or charred, leathery · the center may feel nothing — the nerves are gone · needs grafting
Depth decides the story. Superficial burns hurt and heal. Full-thickness burns destroy the nerve endings, so the center may not hurt at all — that silence is a danger sign, not a comfort.
Illustration: BruceBlaus / Blausen Medical, "1st, 2nd, and 3rd degree burns", CC BY-SA 4.0 (via Wikimedia Commons). Degree chips are page overlays, not part of the artwork.
Burns
Burns — rule of nines
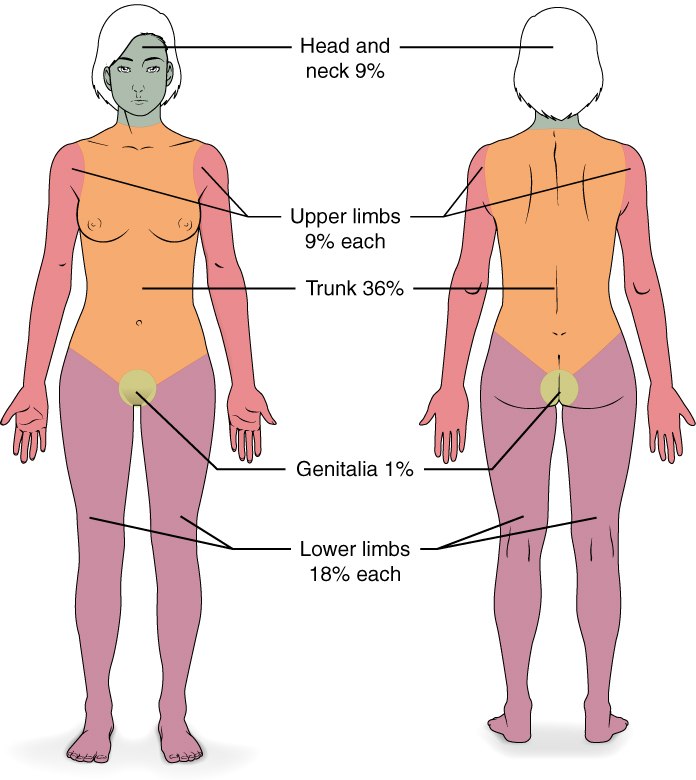
The split
Head & neck 9% · each arm 9% · trunk front 18% · trunk back 18% · each leg 18% (9 front + 9 back) · perineum 1% = 100%
Children differ
A child's head is proportionally larger — use the pediatric (Lund–Browder) chart for kids.
The fastest surface-area estimate in the burn unit. Count in nines — and remember this is the adult chart.
Illustration: OpenStax College, Anatomy & Physiology, CC BY 3.0 (via Wikimedia Commons, "513 Degree of burns"). Labels are part of the original figure.
Medication administration
IM injection sites
1 · Deltoid — upper arm
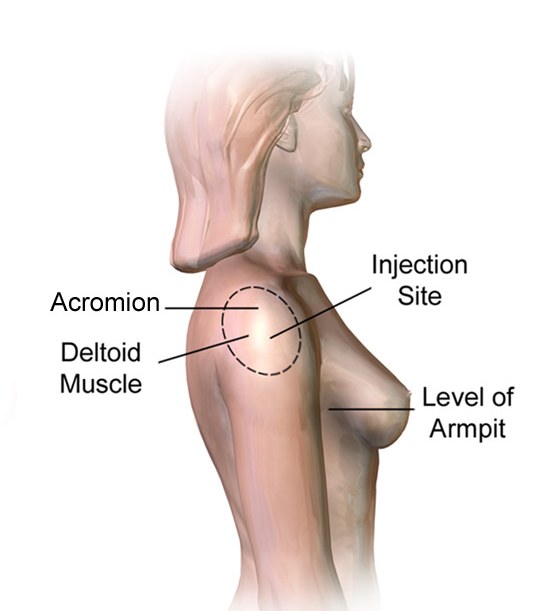
Thickest part of the muscle, about 5 cm (2–3 fingerbreadths) below the acromion. Small volumes only — the bursa sits above, the radial nerve below.
2 · Vastus lateralis — outer thigh
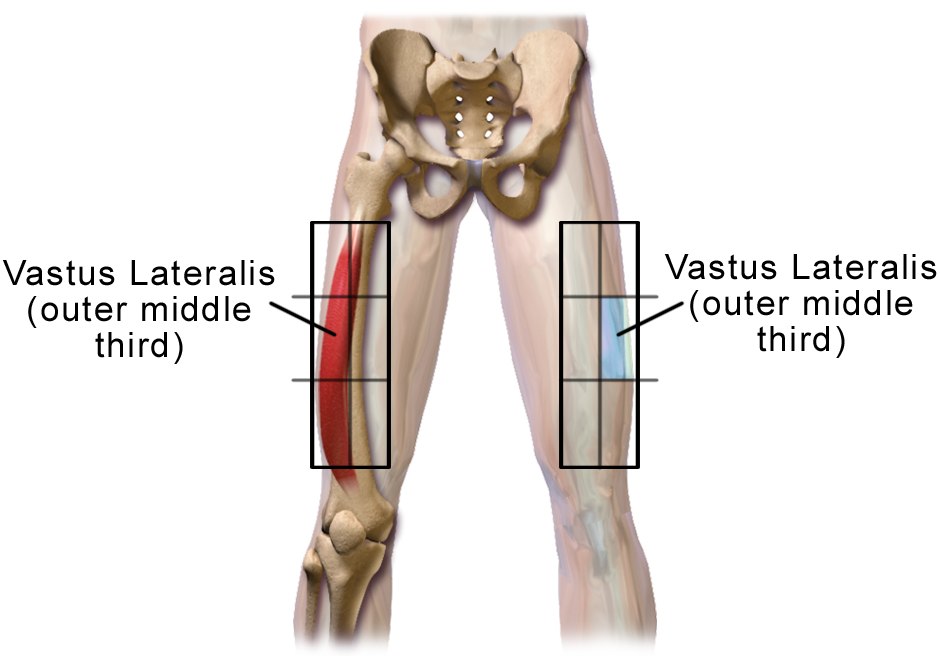
The middle third of the outer thigh, between the greater trochanter and the knee.
First choice for IM adrenaline in anaphylaxis — this muscle absorbs fastest. That is exactly what the app's anaphylaxis lesson teaches.
3 · Ventrogluteal — the hip, by hand landmarks
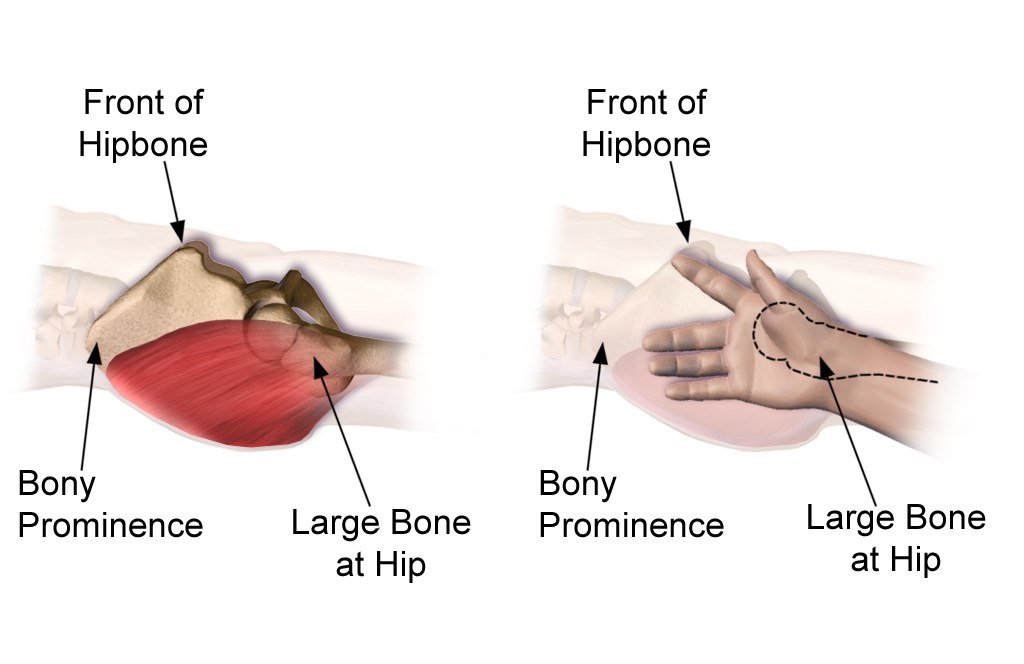
Palm on the greater trochanter (the art's "Large Bone at Hip"), index finger to the ASIS ("Front of Hipbone"), middle finger along the iliac crest — inject inside the V between the fingers. Clear of the sciatic nerve; a safe site for larger volumes.
Landmarks first, needle second. Every safe IM site is found by bone landmarks — acromion, greater trochanter, iliac crest — never by guessing a spot on the skin.
Illustrations: BruceBlaus / Blausen Medical, CC BY-SA 4.0 (via Wikimedia Commons). The deltoid image is cropped from the source's rear-end & deltoid figure; labels are the original artwork.
Cardiac · ECG
ECG — one heartbeat, labeled
One beat, three waves, three intervals. If you can measure the PR and the QRS on a single complex, you can read any strip the exam puts in front of you.
PNLE Companion artwork — waveforms generated from a parametric beat template on a true 25 mm/s · 10 mm/mV grid (same verified waveforms as v1, restyled).
Cardiac · ECG
ECG — the board rhythm patterns
Read every strip the same way: rate, rhythm, P waves, QRS. Two of these six are act-first emergencies — VF gets a shock; asystole gets CPR and epinephrine, never a shock.
PNLE Companion artwork — parametric waveforms, restyled for v2.
Maternal & child
Fetal circulation — the three shunts
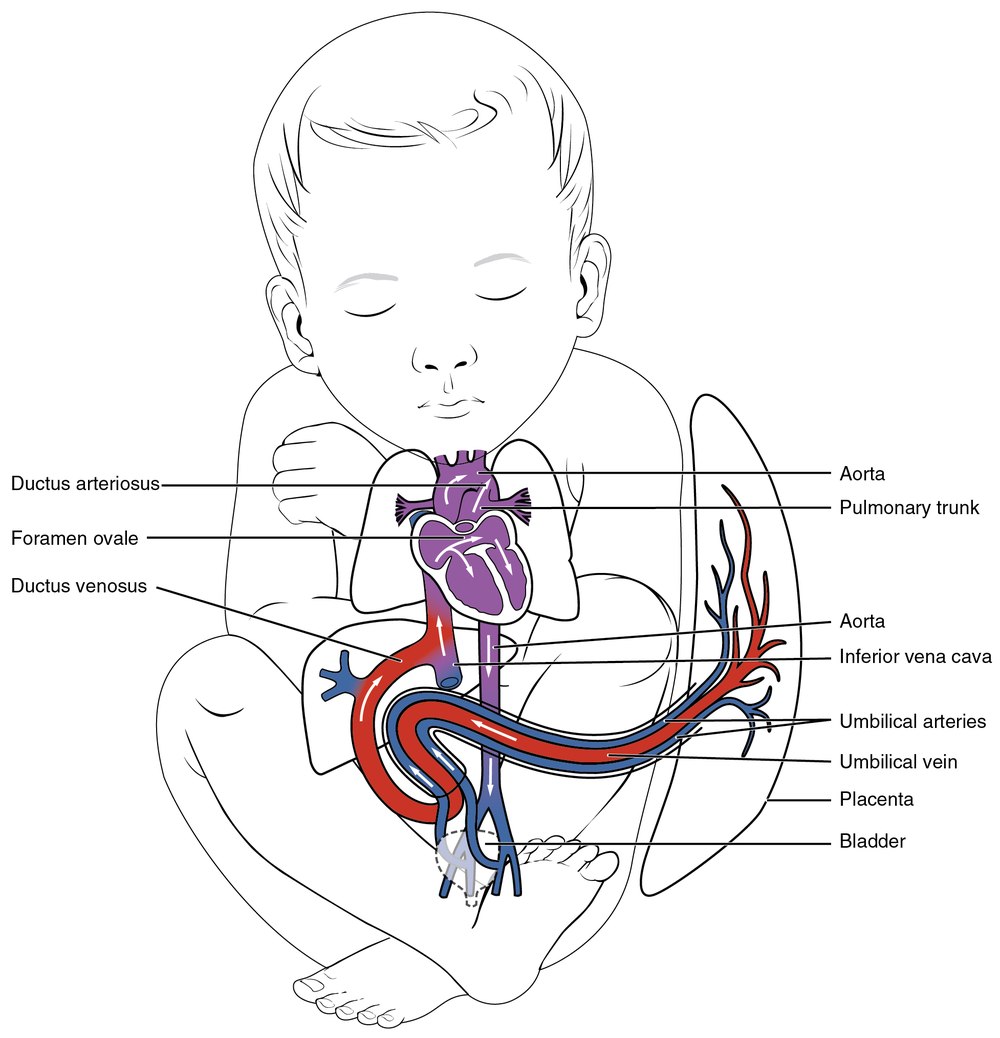
1
Ductus venosus — umbilical vein → inferior vena cava, bypassing the liver
2
Foramen ovale — right atrium → left atrium, bypassing the lungs
3
Ductus arteriosus — pulmonary artery → aorta, bypassing the lungs
OxygenatedMixedDeoxygenated
Before birth, the placenta is the lung. Three shunts route blood around the fluid-filled lungs — and all three are supposed to close once the baby takes its first breaths.
Illustration: OpenStax College, Anatomy & Physiology, CC BY 3.0 (via Wikimedia Commons, "2139 Fetal Circulation"). Labels are part of the original figure; the shunt list below it is ours.